Psoriasis and Eczema: Differences in Symptoms and Care
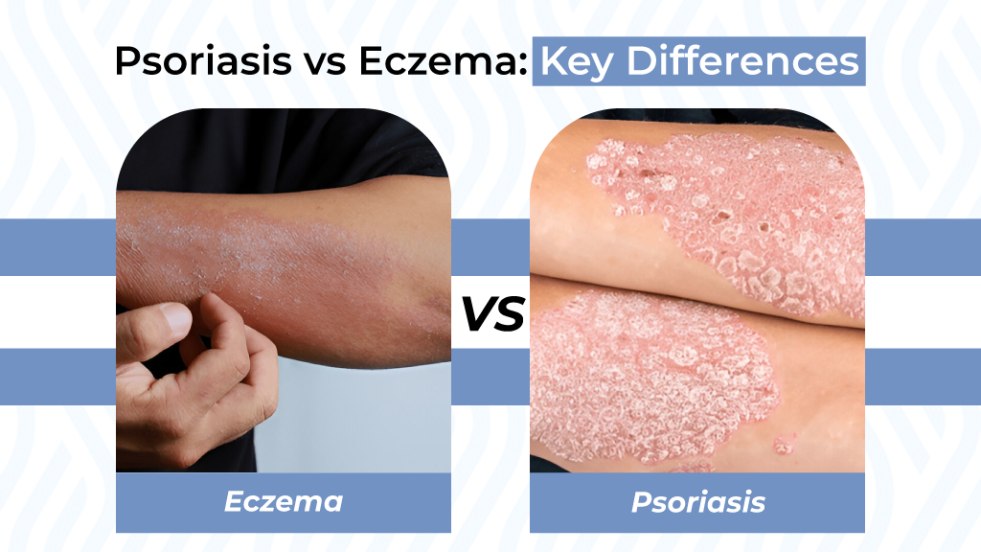
Psoriasis and eczema can both cause itchy, inflamed, scaly skin. Their appearance can overlap, especially after scratching or treatment, but the underlying processes and treatment choices differ. A comparison can help you describe a rash; it cannot reliably diagnose one from a photograph.
Here, eczema refers mainly to atopic dermatitis. For the broader group of conditions called eczema, see our eczema overview.
The conditions involve different patterns of inflammation
Atopic dermatitis involves an interaction between skin-barrier function, immune activity, inherited susceptibility and environmental influences. Dryness and persistent itching are common, and scratching can make the skin rough, cracked or thickened.
Psoriasis is an immune-mediated condition in which skin cells accumulate more quickly than usual. Plaque psoriasis, its most common form, often produces raised, well-defined areas with scale. Other forms may look quite different, so the familiar picture of a thick plaque does not describe every case.
Appearance and location can provide clues
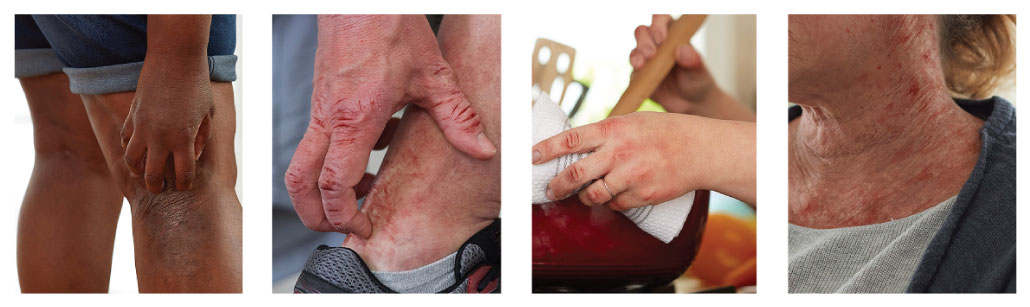
Atopic dermatitis often affects skin folds, the hands, face or neck, although its distribution varies with age. The edges of an inflamed area may be less distinct, and severely irritated skin may crack, ooze or crust.
Plaque psoriasis often involves the scalp, elbows, knees or lower back. Scale can be prominent, but psoriasis in skin folds may appear smoother. Neither location nor the amount of scale is enough on its own to separate the conditions.
Both conditions can look different across skin tones. Inflammation may appear pink or red, purple, gray or darker brown. Thickening, scale, discomfort and changes from your usual skin can be as informative as color.
Itch, nails and joints add useful information
Itching is a major feature of atopic dermatitis, but psoriasis can itch intensely too. Burning or pain can occur in either condition, particularly when the skin is cracked. Symptom severity does not establish the diagnosis or make one condition universally more serious than the other.
Nail pitting, separation or thickening may occur with psoriasis, although other conditions also affect nails. New joint stiffness, swelling or pain in someone with psoriasis deserves timely medical assessment because psoriatic arthritis needs its own treatment.
A clinician looks beyond a single patch
Assessment may include the history of the rash, its distribution, nail findings, family history and treatments already tried. A clinician may occasionally need a skin sample or other testing when the appearance is uncertain. Bring photographs if the rash changes between visits.
Neither condition is contagious. Both may have periods of improvement and recurrence, and either can have a substantial effect on sleep or quality of life. A rash that fails to respond as expected should be reassessed instead of repeatedly treated under an assumed diagnosis.
Skin comfort and medical treatment serve different purposes
Gentle washing and regular moisturizer can help dry skin feel more comfortable in either condition. Dermal Defense Moisturizing Cream provides face and body hydration with glycerin and petrolatum. It does not treat the immune processes of psoriasis or replace prescribed eczema care.
Topical medicines, light treatment and systemic therapies may be considered according to the diagnosis and severity. Follow the plan for your condition and the specific body area being treated. Avoid using a strong treatment prescribed for one area on the face or skin folds without advice.
There is no general instruction to eliminate eggs, dairy, peanuts or other major foods merely because a rash resembles eczema or psoriasis. Discuss a suspected food reaction or a dietary concern with an appropriate clinician.
Seek help for a severe or changing flare
Arrange review if symptoms are interfering with sleep, spreading or not improving with the agreed plan. Widespread painful inflammation, fever, rapidly worsening skin or signs of infection need prompt assessment. Mention joint symptoms even if the skin changes seem mild.
References: NIAMS: psoriasis; atopic dermatitis.

- Eczema and Swollen Lymph Nodes: Causes and When to Seek Care - March 24, 2026
- Eczema-Prone Skin and Moisture Loss: Understanding the Skin Barrier - March 24, 2026
- Eczema and the Immune System: Inflammation and Barrier Function - February 18, 2026