Understanding Eczema: Types, Symptoms and Care

Eczema is a name for a group of inflammatory skin conditions. Itching, dryness, roughness and changes in skin color are common, but the cause and the right treatment depend on the type. Atopic dermatitis is the condition people most often mean when they say “eczema.”
This overview explains the main distinctions and points to more detailed guides. It is a starting point for understanding a diagnosis, rather than a way to identify every rash yourself.
Symptoms vary with the person and the stage of a flare
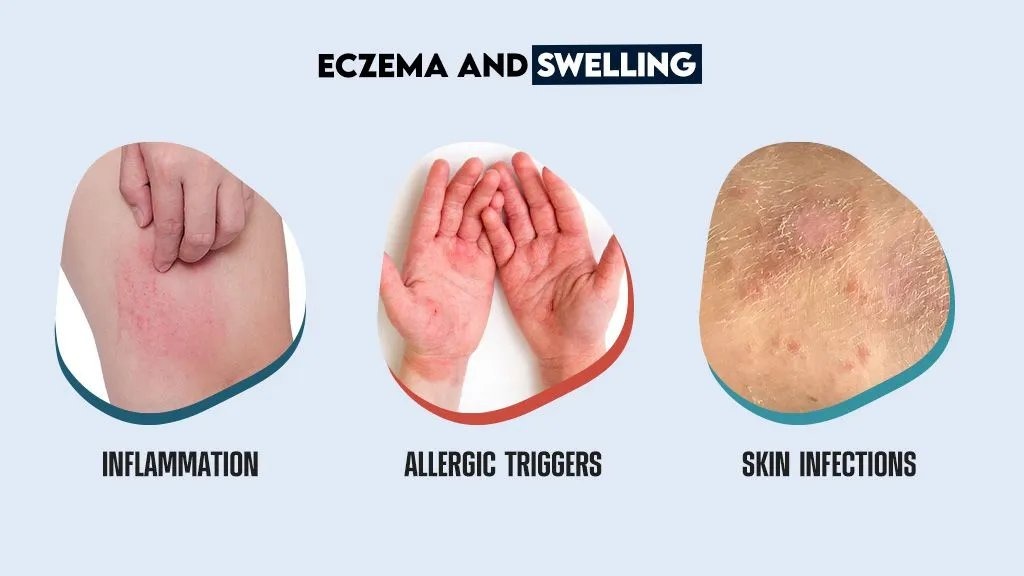
Eczema may cause dry, scaly patches, persistent itching, small bumps, cracks or thickened skin from repeated rubbing. Active inflammation can feel warm or swollen. Some patches ooze, although oozing does not by itself prove infection.
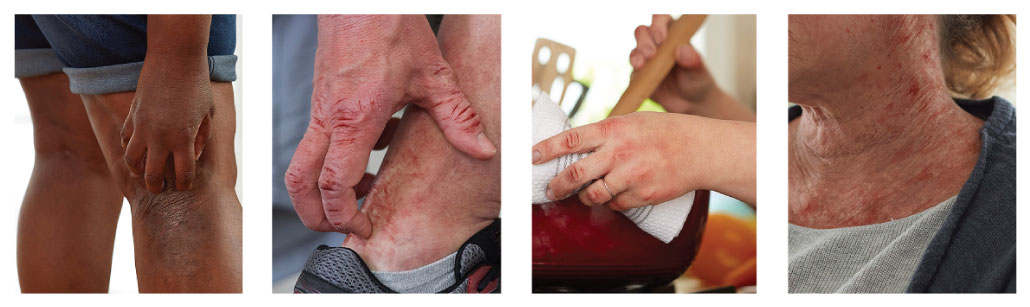
Color also varies. Inflamed skin may appear pink or red on lighter skin, and purple, gray or darker brown on more deeply pigmented skin. Lighter or darker marks can remain after inflammation improves. Our guide to eczema across skin tones explains why texture and symptoms matter alongside color.
A flare is a period when symptoms become more active. Improvement between flares does not always mean the skin needs no ongoing care. The pattern, affected areas and duration help a clinician distinguish eczema from other conditions.
Atopic dermatitis involves the barrier and immune system
Atopic dermatitis develops through interacting influences, including inherited susceptibility, skin-barrier function, immune signaling and the environment. A less effective barrier can lose water more readily, while inflammation can further disturb its function. This interaction helps explain recurring dryness and sensitivity.
A family history of eczema, asthma or allergic rhinitis can be relevant, but it is not required. Not everyone has the same genetic changes or triggers. For a closer explanation, see inherited eczema risk and skin-barrier water loss.
Heat, sweat, dry air, friction, fragrance and other irritants may worsen symptoms. Stress can also play a part. A trigger for one person may be harmless to another, so a long avoidance list is less useful than identifying a consistent personal pattern.
Common forms of eczema have different defining features
Atopic dermatitis
Atopic dermatitis often starts in childhood, but it can persist or begin in adulthood. It commonly causes recurring itchy, dry patches. The distribution changes with age and may include the face, neck, hands or skin folds. Treatment aims to control inflammation and itch while supporting the skin barrier.
Contact dermatitis
Contact dermatitis develops when an exposure damages the skin or triggers a delayed allergic reaction. Irritant contact dermatitis can follow repeated wet work, detergents or friction. Allergic contact dermatitis may involve a substance such as nickel, fragrance or a preservative. Identifying and avoiding the relevant exposure is central to care; our comparison with atopic dermatitis explains the differences.
Dyshidrotic eczema
Dyshidrotic eczema produces small, often intensely itchy blisters on the palms, sides of the fingers or soles. The skin may peel or crack as an episode settles. Blisters on hands or feet can have other causes, so recurrent or painful episodes should be assessed rather than diagnosed by appearance alone.
Neurodermatitis
Neurodermatitis, also called lichen simplex chronicus, involves a persistent itch–scratch cycle that can produce a thickened patch. It often affects a limited area. Care focuses on identifying the source of itch and interrupting the cycle; telling a person simply not to scratch is rarely sufficient.
Seborrheic dermatitis
Seborrheic dermatitis often affects oily areas such as the scalp, eyebrows, sides of the nose and beard. Flaking and inflammation may involve the skin’s response to Malassezia yeast. Its treatment differs from that of atopic dermatitis and may include an appropriate antifungal or medicated product. A moisturizer can support dryness but does not replace that treatment.
Nummular eczema
Nummular eczema creates round or oval patches that may be dry, itchy, crusted or weeping. Its shape can resemble a fungal infection such as ringworm. A clinician may need to distinguish these possibilities before recommending treatment, particularly when a round rash expands or does not improve.
Stasis dermatitis
Stasis dermatitis occurs in association with poor venous circulation, often in the lower legs. Swelling, itching, discoloration and sometimes wounds may occur. Skin care alone does not address the circulation problem. Compression or other circulation measures should be selected with a clinician, especially when the diagnosis or blood supply is uncertain.
Diagnosis guides the treatment plan
A clinician considers the history, distribution and appearance of the rash, along with exposures and previous treatment. Depending on the pattern, assessment may include testing for contact allergy, infection or another condition. Photographs help document changes, but similar-looking rashes may need very different care.
Moisturizing and avoiding irritation support many forms of eczema, while treatment of inflammation or an underlying cause is individualized. Prescription medicines, light therapy or other treatments may be appropriate. Do not transfer a treatment plan for one type of eczema to another person or body area without advice.
Daily skin care supports comfort
Use gentle cleansing, lukewarm water and regular moisturizer. A cream or ointment that you tolerate can help dry skin retain moisture, particularly after washing. Our daily eczema routine gives the practical sequence without repeating a separate regimen for every diagnosis.
Dermal Defense Moisturizing Cream is a fragrance-free face and body moisturizer with glycerin and petrolatum. It provides hydration and moisture support. It is not a medicated treatment for the different causes of eczema.
Changing symptoms deserve attention
Seek review when a rash is new, uncertain, worsening or disrupting sleep and daily activities. Increasing pain, warmth, pus, spreading inflammation or fever can indicate infection. Painful clusters of blisters, especially with fever or eye involvement, require urgent assessment.
Eczema itself is not contagious. If you are concerned about transmission or infection, see eczema and contagious skin conditions. A clear diagnosis is more useful than assuming every itchy patch is the same condition.
References: NIAMS: atopic dermatitis; American Academy of Dermatology: contact dermatitis.

- Eczema and Swollen Lymph Nodes: Causes and When to Seek Care - March 24, 2026
- Eczema-Prone Skin and Moisture Loss: Understanding the Skin Barrier - March 24, 2026
- Eczema and the Immune System: Inflammation and Barrier Function - February 18, 2026